
Sudden Vision Loss and EECP: What Does the Evidence Say?
Sudden loss of vision in one eye is an emergency and must be assessed immediately. Blockage of the eye's artery is regarded as a type of stroke. EECP has been studied in this situation; however, the evidence is limited and contradictory.
- Non-surgical
- 35 Sessions
- Painless
In brief
It may support treatment in patients with sudden vision loss and may help vision recover.
Time is critical in sudden vision loss. Go to the emergency department or an eye emergency unit without waiting.
In one controlled study, EECP did not improve vision in an optic nerve disease causing sudden vision loss.
Evidence is limited and contradictory. EECP does not replace emergency treatment; it may, however, be discussed afterwards and in selected patients.
What Happens in Sudden Vision Loss?
The eye depends on very thin vessels that feed the retina. When one of these vessels is blocked or the blood supply to the optic nerve is impaired, vision can drop suddenly. The American Heart Association describes retinal artery blockage as a type of stroke.
Retina
The retina is the thin layer of the eye that senses light. Without blood supply, its cells can be damaged within a short time.
Optic nerve
The optic nerve carries the image to the brain. Impaired blood supply to it is called ischemic optic neuropathy and usually causes sudden vision loss.
Carotid arteries
Blood reaches the eye through the carotid arteries in the neck. Fragments breaking off plaques there can block an eye artery.
Hover over or tap the cards: the related area is highlighted in the illustration.
Heart and rhythm
Clots formed in the heart can also travel to an eye artery. That is why the heart and its rhythm are checked after sudden vision loss.
Brain
Retinal artery occlusion shares risk factors with stroke. A possible stroke risk is therefore also investigated afterwards.
Risk factors
Blood pressure, sugar, cholesterol and smoking also affect the eye's blood vessels. Guidelines recommend prompt screening and treatment of these risks.
Eye Circulation: Before and With EECP
The comparison below shows in simple form the circulatory support targeted with EECP. An effect on eye disease has not been proven.
Sudden vision loss
- Sudden vision decrease in one eye
- Insufficient blood supply to the retina or optic nerve
- Heart and vascular risk factors
Circulatory support after emergency treatment
- Increased flow in the head and neck vessels is targeted
- Ophthalmologist follow-up continues
- Risk factors are treated
Schematic illustration. EECP does not replace emergency treatment for sudden vision loss.
How Is EECP Applied?
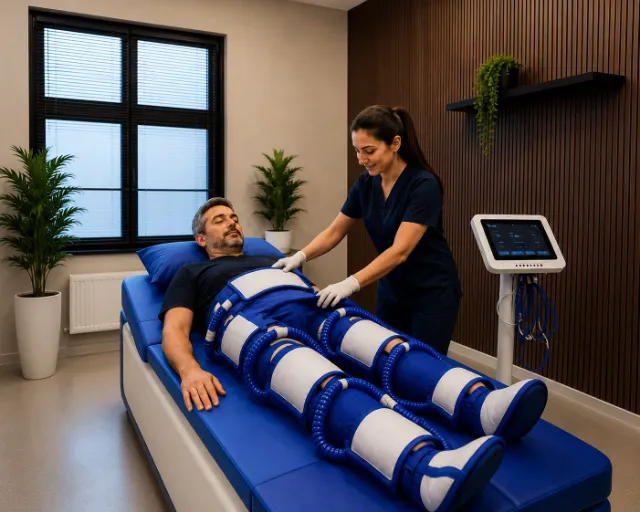
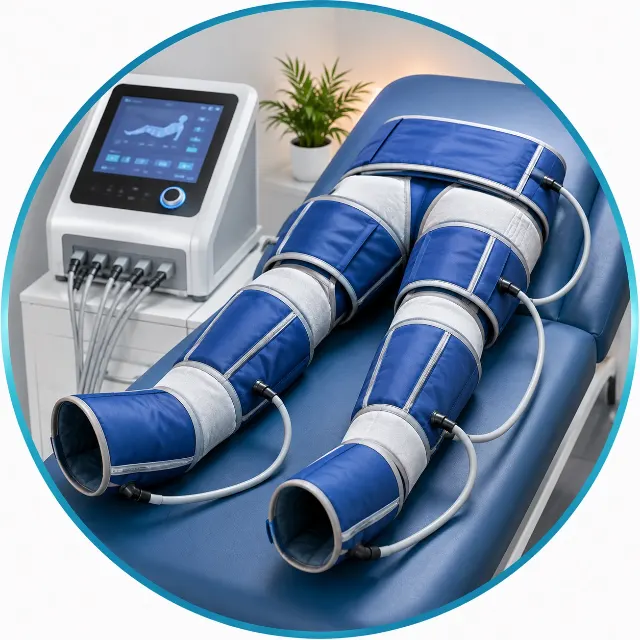
During treatment you lie down and rest. The device monitors your heart rhythm with an ECG and controls the cuffs accordingly.
Cuffs inflate
While the heart relaxes, the cuffs on the calves, thighs and buttocks inflate in sequence: first the calves, then the thighs and buttocks.
Blood is directed toward the head
The pressure that rises while the heart relaxes also reaches the head and neck vessels. Its effect on eye circulation varies from person to person.
The heart's workload is reduced
The pressure is released just before the heart contracts, so the heart can pump more easily. This cycle repeats with every heartbeat.
Vision is monitored
Visual acuity and visual field before and after the course are compared by your ophthalmologist.
What Have Studies Shown?
Below we summarize the key information from studies and guidelines. Response varies from person to person.
Emergency
The American Heart Association defines retinal artery occlusion as a medical emergency.
Rapid evaluation
The guideline recommends that these patients be evaluated and referred for treatment without delay.
Non-surgical and painless
It is applied externally with cuffs; you lie down and rest throughout the session.
Tolerability
In a study of patients with optic nerve disease, EECP was well tolerated by all patients.
Expert opinion
Experts in China suggest starting EECP as early as possible after retinal artery occlusion.
Risk factors
The guideline recommends urgent screening and treatment of vascular risk factors in these patients.
Who Is It Suitable For, and Who Not?
Urgent eye and neurology evaluation comes first; stroke screening and risk factors are addressed. Only after this stage can EECP be discussed together with your ophthalmologist and our cardiologist.
✓May be suitable
- Patients with retinal vascular occlusion whose emergency evaluation and treatment are complete
- Patients under ophthalmologist follow-up who are suitable from a cardiovascular standpoint
- Patients with narrowing in the neck arteries who wish to support vascular health
- Patients already eligible for EECP due to heart or vascular disease who have had an eye vessel problem in the past
✕Not suitable
- Newly started vision loss: go to the emergency room immediately first
- Severe aortic valve regurgitation
- Aortic aneurysm
- Active deep vein thrombosis, vein inflammation
- Uncontrolled high blood pressure
- Severe rhythm disorders
- Marked bleeding tendency and pregnancy
How Does the Treatment Process Work?
Blood pressure and pulse are checked before every session. At the end of the course, results are reviewed with our cardiologist. For eye patients, vision measurements are taken on your ophthalmologist's schedule.
Frequently Asked Questions About Sudden Vision Loss and EECP
What should I do first if I lose vision suddenly?
Go to the emergency room or an eye emergency unit without waiting. The American Heart Association defines this as a medical emergency.
Will EECP restore my vision?
We have not read a controlled study showing this. In a controlled study on optic nerve disease, EECP did not improve vision more than the control group.
Why are the heart and brain examined too?
Retinal artery occlusion is a type of stroke and shares the same risk factors. That is why the heart, rhythm and neck arteries are also evaluated.
When can EECP be considered?
Only after emergency evaluation and treatment are complete, and together with your ophthalmologist. Because the evidence is limited, expectations are shared openly from the start.
Will I keep taking my medication?
Yes. You should continue your medication as recommended by your cardiologist. Any change to medication is decided only by your doctor.
How many sessions are needed?
The standard course is 35 sessions: 5 days a week, 60 minutes per session. The plan is aligned with your ophthalmologist's follow-up, and vision measurements are repeated regularly.
You May Also Be Interested In




Contact us for a free preliminary assessment
If you are experiencing sudden vision loss, go to the emergency room immediately first. If you are curious about EECP after your treatment, contact us with your eye and vascular test results; we will discuss expectations openly.
- Non-surgical
- Painless
- Under medical supervision
- Nicosia, Cyprus